Natural smile illustrating cosmetic dental bonding for chipped or uneven teeth

Dental bonding is one of the most conservative ways to improve a smile. A small chip, an uneven edge, a modest gap, or a tooth that looks slightly out of proportion can sometimes be corrected without preparing the tooth for porcelain.

But patients usually have a second question: How long will the bonding last?

It is a fair question, and I would rather give a realistic answer than promise a number of years that no dentist can guarantee. Composite resin is repairable and versatile, but it is not indestructible. Its longevity depends on where it is placed, how the teeth meet, the size of the restoration, and how it is maintained.

How Long Does Dental Bonding Last?

As a general planning estimate, cosmetic bonding may last roughly 3 to 10 years before it needs polishing, repair, or replacement, and some restorations last longer. That is a broad range, not an expiration date. Small, well-supported repairs can behave differently from extensive bonding across multiple front teeth.

Some bonding requires a minor touch-up after a few years. Other bonding remains functional and attractive for much longer. Importantly, needing a polish or a small repair does not mean the entire restoration has failed.

What I look at is not just how old the bonding is, but whether it is still smooth, intact, well sealed, and compatible with the bite.

What Makes Dental Bonding Last Longer—or Wear Out Faster?

Where the bonding is located

Bonding placed on a low-stress area of a tooth may experience less mechanical loading than bonding used to rebuild an incisal edge that contacts the opposing teeth during chewing or grinding.

Front teeth may be highly visible, but they also do work. If the restoration is repeatedly struck during normal function, the risk of chipping increases.

How much tooth is being rebuilt

Adding a small amount of composite to smooth an uneven edge is different from replacing a large missing corner. The more material we need to add—and the less natural tooth available to support it—the more carefully we need to consider the long-term mechanics.

Grinding, clenching, and bite relationships

Someone who clenches or grinds can place substantial forces on bonding, veneers, crowns, and natural teeth alike. A protective nightguard may be appropriate in selected cases, but first we need to evaluate the bite and the source of the wear.

Sometimes the best way to protect a cosmetic result is to address the tooth position or bite before adding material.

Habits and maintenance

Chewing ice, biting pens, using teeth to open packaging, or repeatedly biting hard objects can damage bonded edges. Routine brushing, flossing, and professional examinations help us identify roughness, staining, or marginal problems early.

Does Dental Bonding Stain?

Yes. Composite resin can develop surface staining and changes in polish over time. Coffee, tea, tobacco, certain foods, surface roughness, and individual habits can all affect appearance.

That does not mean every discolored restoration needs replacement. Sometimes professional polishing can improve the surface. In other situations, staining at the edge of the bonding or a deeper color mismatch may require repair.

There is an important whitening distinction: peroxide products can lighten natural teeth, but they do not reliably change the original shade of composite resin. We covered that in Can You Whiten Veneers, Crowns, or Bonding?

If you plan to whiten your natural teeth, it often makes sense to discuss that before selecting the final shade of new cosmetic bonding.

Can Chipped Bonding Be Repaired Instead of Replaced?

Often, yes. Repairability is one of composite bonding’s advantages. If a small corner chips and the remaining material and tooth are healthy, it may be possible to roughen, condition, and add new composite to restore the shape.

But I would not promise that every chipped restoration can be patched indefinitely. A recurring fracture may indicate a bite problem, insufficient support, a crack in the underlying tooth, or a restoration that is being asked to do too much.

When bonding breaks repeatedly in the same place, simply adding more material without investigating why is unlikely to be the best long-term approach.

When Should Bonding Be Replaced?

Age alone is not a reason to remove bonding. I consider replacement when the restoration has a significant fracture, persistent discoloration that cannot be improved conservatively, defective margins, decay around it, or an appearance that no longer meets the patient’s goals.

Sometimes the most conservative treatment is no treatment at all. If a small bonded area is functioning well and the color difference is minor, there may be no clinical benefit to removing it.

When replacement is appropriate, we should aim to preserve as much sound enamel and dentin as possible. Every restorative procedure has a cost in tooth structure, even when the material itself is considered conservative.

Bonding vs. Veneers: Which Lasts Longer?

Porcelain veneers generally offer greater long-term color stability and can be a good option when multiple teeth require substantial changes in shape, proportion, or shade. Composite bonding is typically easier to repair and may require less removal of healthy tooth structure.

Neither is automatically the right choice. Porcelain is not immune to fracture or eventual replacement, and it is often more invasive and more expensive initially.

For a small chip on an otherwise healthy tooth, bonding may be exactly what I would choose. For extensive, repeated repairs or a more complex smile redesign, porcelain may deserve consideration. Our article on dental bonding versus veneers explains the tradeoffs in greater detail.

Could Invisalign Help Bonding Last Longer?

In selected cases, yes. If tooth position creates an unfavorable contact or makes it necessary to build out a large amount of composite just to disguise crowding, orthodontic movement may allow a more conservative and better-supported final restoration.

That does not mean every patient who wants bonding needs Invisalign. It means we should look at the cause of the cosmetic concern before deciding on the material.

If tooth movement is part of the discussion, our Invisalign timeline guide explains what affects the duration of treatment.

How Much Does It Cost to Maintain or Replace Bonding in NYC?

The cost depends on whether the restoration needs simple polishing, a limited repair, or complete replacement. A tiny chipped edge is not the same procedure as rebuilding several front teeth.

I would be cautious about using a single online per-tooth price as a substitute for an examination. Fees vary with the amount of composite, the complexity of the shape and bite, and whether other dental problems must be addressed first.

The more useful financial question is the lifetime maintenance of the treatment. A conservative, repairable restoration may be a very good value even if it needs an occasional touch-up. Conversely, repeatedly replacing large restorations without correcting the cause of failure can become expensive.

How to Care for Dental Bonding

  • Brush twice daily with a soft-bristled toothbrush and fluoride toothpaste, and clean between your teeth every day.
  • Keep routine dental visits so small chips, rough margins, or staining can be evaluated early.
  • Avoid using bonded teeth as tools or biting hard nonfood objects.
  • Discuss clenching or grinding rather than assuming a nightguard is needed for everyone.
  • Ask before using abrasive whitening products or DIY polishing methods.
  • Call your dentist if a restoration feels sharp, loose, painful, or suddenly changes the way your teeth meet.

These steps help protect both the bonding and the natural tooth beneath it. They do not guarantee a particular lifespan, but they reduce avoidable problems.

Frequently Asked Questions

Can dental bonding last 10 years?

Yes, some bonding can last a decade or longer, particularly when it is well supported and protected from excessive forces. Other restorations need attention sooner. The location and size of the bonding matter more than a universal time limit.

Does bonding need to be redone every few years?

Not automatically. We replace or repair bonding based on its condition, appearance, and function—not simply because a calendar date has passed.

Can a dentist polish old bonding?

Often, if the issue is superficial staining or a loss of surface gloss. Deeper discoloration, fractures, or defective margins may require more than polishing.

Will whitening strips whiten dental bonding?

No. Whitening strips may lighten natural teeth, but composite resin does not reliably bleach. This can create a visible mismatch, particularly on front teeth.

Is bonding permanent?

Bonding is a durable restoration, but it should not be described as permanent or maintenance-free. It can wear, chip, stain, and sometimes need repair or replacement.

The Bottom Line

Dental bonding is valuable precisely because it can solve many small cosmetic problems without committing a healthy tooth to a more extensive restoration.

Its lifespan is variable. A reasonable planning range is several years, often roughly three to ten, with some restorations lasting longer and others needing earlier maintenance. The real goal is not to make a material last forever. It is to choose a treatment that is appropriate for the tooth, preserve healthy structure, and maintain the result thoughtfully.

Dr. Andrew Frangella provides cosmetic and general dentistry at Frangella Dental in Midtown Manhattan. If you have chipped, stained, or aging bonding, an examination can help determine whether polishing, repair, replacement, or no treatment is the most sensible next step.

Woman demonstrating a transparent dental aligner, illustrating Invisalign treatment options and costs in NYC

“How much does Invisalign cost in NYC?” is a reasonable question. But it is also a question that deserves more than a single advertised price.

Two people can both want straighter front teeth and have very different treatment needs. One may have mild spacing that can be corrected with a relatively limited series of aligners. Another may have a bite problem, difficult rotations, or a history of previous orthodontic treatment that makes the plan more involved.

When I talk about Invisalign cost, I want patients to understand not just the fee, but what treatment actually includes—and whether moving the teeth is the most conservative way to achieve their goals.

How Much Does Invisalign Cost in NYC?

Published 2026 NYC Invisalign estimates span roughly $3,500 to $11,000, with some Manhattan practices charging more than $10,000 for comprehensive treatment. The lower end can reflect limited treatment or promotional pricing, while comprehensive and complex cases often command higher fees. These are published market ranges, not a Frangella Dental quote; there is no authoritative citywide fee survey. See Wall Street Orthodontics’ 2026 NYC price guide and Sachar Dental’s Manhattan fee ranges for examples. Limited cases may be less; complex treatment can exceed that range. These are illustrative market estimates, not a Frangella Dental fee schedule or a quote. Actual fees vary by practice, case complexity, and what is included.

I would not make a treatment decision from that number alone. A quote for limited front-tooth alignment is not equivalent to a comprehensive plan that also addresses the bite. The important questions are what we are correcting, what is included, and what happens if the teeth need additional refinement.

What Determines the Price of Invisalign?

1. The complexity of tooth movement

Small amounts of crowding or spacing can sometimes be corrected with fewer aligners and less involved planning. Significant rotations, bite discrepancies, vertical movements, and coordination between the upper and lower arches may require more stages and monitoring.

More trays do not automatically mean better treatment, but the movements required have a real effect on the treatment plan.

2. Limited versus comprehensive treatment

Some patients primarily want to improve a small cosmetic issue. Others need broader correction of tooth position and occlusion. A limited plan can be appropriate in selected cases, but it should not be used to disguise a bite problem that ought to be addressed.

I would rather explain why comprehensive treatment is—or is not—necessary than fit everyone into the same advertised package.

3. Refinements and follow-up visits

Teeth are biological structures, not objects that move perfectly along a digital animation. Sometimes they do not track exactly as planned. Additional scans and refinement aligners may be needed to finish treatment properly.

Before starting, ask whether refinements are included, what limits apply, and what additional fees might arise if treatment extends beyond the initial series.

4. Retainers and long-term maintenance

Active alignment is only part of orthodontic care. Once teeth have moved, retainers are needed to help keep them there. Ask whether the initial retainers are included, what replacements cost, and what long-term wear is expected.

A quote that excludes retention may look less expensive initially without representing the complete cost of maintaining the result.

How Long Does Invisalign Treatment Take?

For many adults, active treatment is measured in months, not weeks. A broad planning range may be about six to eighteen months, although simple cases can be shorter and complex cases longer. We covered the variables in detail in our guide to Invisalign treatment timelines.

What matters is the amount and type of movement required, the way the teeth respond, and whether aligners are worn consistently. Many plans call for approximately 20 to 22 hours of daily wear. If aligners spend too much time out of the mouth, teeth may not track and the calendar can stretch.

A shorter advertised timeline is not necessarily a better treatment plan.

Is Invisalign More Expensive Than Traditional Braces?

It depends on the case and the provider. The cost ranges overlap, and one option is not universally cheaper.

Clear aligners offer removability and a less visible appearance, but they require consistent wear and may not be ideal for every orthodontic movement. Fixed appliances have their own advantages and limitations.

The choice should begin with what will predictably correct the teeth and bite, not just which appliance looks more appealing in an advertisement. Our Invisalign versus braces comparison explores those tradeoffs.

Will Dental Insurance Pay for Invisalign?

Some dental plans include orthodontic benefits that may apply to clear aligners, particularly when the patient meets the plan’s eligibility requirements. Others exclude adult orthodontics, impose age limits, have waiting periods, or apply a lifetime orthodontic maximum.

Even when a plan offers orthodontic benefits, the amount paid is not necessarily the same as the amount listed in the benefit summary. Prior treatment, annual or lifetime limits, and network provisions may affect reimbursement.

Before treatment, we can review the available benefit information and provide an estimate, but the insurer makes the final coverage determination. Patients should also ask about payment arrangements and any potential use of eligible HSA or FSA funds under their plan rules.

What Should Be Included in an Invisalign Quote?

Rather than comparing one headline number with another, ask for the details in writing. A useful quote should clarify:

  • Whether the plan is limited or comprehensive and which teeth and bite problems it addresses.
  • What records, scans, and treatment-planning visits are included.
  • Whether attachments, enamel reduction when appropriate, and routine progress visits are included.
  • How refinements are handled and whether additional aligners could generate a fee.
  • What happens if a patient does not wear aligners consistently or treatment needs to be extended.
  • Whether retainers and follow-up retention visits are included.
  • How insurance estimates, payment terms, and possible additional services are presented.

A lower price may be entirely appropriate for a limited case. But it is not a bargain if the plan does not address the problem that actually needs correction.

Do You Need Invisalign Before Veneers or Bonding?

Sometimes orthodontics is the most conservative first step in cosmetic dentistry. If teeth are crowded, rotated, or positioned poorly, moving them can improve the smile without removing healthy enamel to disguise the position with porcelain.

In other situations, the teeth are well aligned and the concern is a chip, worn edge, shape, or color. Those problems may be better treated with bonding, whitening, or a carefully planned veneer rather than orthodontics.

We recently discussed this distinction in our bonding versus veneers article. My approach is to identify the actual problem first, then choose the least invasive treatment that can solve it predictably.

How Digital Scanning Helps Us Plan Invisalign

At Frangella Dental, we use an iTero digital scanner to capture three-dimensional records of the teeth. Those records help us evaluate alignment, communicate the proposed movements, and plan treatment.

Digital treatment simulations are useful, but they are not guarantees. We still need to assess periodontal health, the bite, existing restorations, and whether the proposed movements are biologically realistic.

You can read more about our workflow in how we use iTero at Frangella Dental.

What About Mail-Order or Direct-to-Consumer Aligners?

The appeal is obvious: lower advertised prices and fewer office visits. But orthodontics involves more than a sequence of plastic trays.

Before teeth are moved, we need to know whether the gums, bone support, roots, restorations, and bite can accommodate the planned movement. During treatment, someone needs to evaluate whether teeth are tracking and whether the plan should change.

I am not suggesting that every patient needs a complicated treatment program. I am saying that diagnosis and supervision are part of the value of orthodontic care, and should be considered when comparing costs.

Frequently Asked Questions About Invisalign Cost

Is $5,000 a reasonable price for Invisalign in NYC?

It can fall within commonly advertised market ranges, but whether it is reasonable for you depends on the complexity of the case and exactly what is included. A fee cannot be judged properly without the treatment plan.

Can I get Invisalign for just my top or bottom teeth?

In selected situations, limited single-arch treatment may be considered. But upper and lower teeth function together. Moving one arch can affect the bite, so this is a clinical decision rather than simply a way to cut the price in half.

Does Invisalign cost more if I need refinements?

That depends on the treatment agreement and aligner plan. Ask before starting whether refinements are included and under what circumstances additional charges may apply.

Do I have to wear retainers forever?

Long-term retention is generally necessary to maintain orthodontic alignment. The type of retainer and wear schedule are individualized, but it is wise to plan for ongoing retainer use and occasional replacement.

The Bottom Line

Invisalign cost in NYC is not one fixed number. The amount and type of tooth movement, the bite, monitoring, refinements, and retention all affect what a complete treatment plan should include.

If you are comparing quotes, bring the questions—not just the prices. I want you to understand what we are correcting, why we are recommending a particular approach, and what a realistic result requires.

The best Invisalign treatment is not necessarily the fastest or the least expensive on paper. It is the one that moves the teeth predictably, protects the bite, and leaves you with a result you can maintain.

Dr. Andrew Frangella provides Invisalign and cosmetic dentistry at Frangella Dental in Midtown Manhattan. For an individualized treatment evaluation and fee estimate, contact our office to schedule a consultation.

“Do I really need a crown, or can you save more of my tooth?” It is a question I wish more patients asked.

A tooth with a large filling, a crack, or damage from decay may need something stronger than another routine filling. But that does not automatically mean every remaining surface should be covered with a full crown. Sometimes an onlay—or another partial-coverage restoration—can protect the tooth while preserving more healthy structure.

The decision is not simply crown versus onlay. It is about how much sound tooth remains, where the tooth is weakened, how your bite loads it, and what gives that particular tooth the most predictable future.

Crown vs. Onlay: What’s the Difference?

A dental crown covers the prepared tooth circumferentially and generally restores the full chewing surface. It can be appropriate when a tooth has extensive damage, multiple weakened walls, a substantial fracture, or limited remaining structure.

An onlay is an indirect restoration that replaces part of the chewing surface and covers one or more cusps—the raised portions of a back tooth. It can provide cuspal protection without necessarily reducing all the surfaces of the tooth as a full crown would.

An inlay stays within the cusps. A direct filling is placed and shaped in the mouth, whereas crowns, onlays, and inlays are commonly fabricated outside the mouth from a digital scan or impression, then bonded or cemented in place.

These are descriptions of restoration designs, not rankings of quality. A well-selected crown can be the conservative decision when an onlay would leave too little reliable tooth structure.

Why Preserving Natural Tooth Structure Matters

Enamel and dentin are not renewable building materials. Once removed, they do not grow back. That is why I want to avoid unnecessary reduction of healthy tooth structure whenever a less extensive restoration can predictably solve the problem.

But “minimal drilling” is not a treatment plan by itself. A tooth that is already undermined by a large filling may have thin cusps that flex or fracture under chewing forces. Preserving those fragile walls just to say we saved more tooth can be a mistake.

The goal is to preserve useful, healthy, supportable tooth structure while protecting what remains.

When Might an Onlay Be a Good Choice?

An onlay is worth considering when a back tooth has a large or failing filling, one or more weakened cusps, or a defect that needs indirect coverage—but still has enough strong tooth structure for a reliable partial restoration.

For example, imagine a molar with a broad old filling and a weakened chewing cusp, but with otherwise sound outer walls. Depending on the bite, crack pattern, moisture control, and remaining enamel, a bonded ceramic onlay may restore the damaged area without the circumferential preparation required for a crown.

Another patient may have an almost identical-looking filling but a crack extending toward the gumline or significant damage to multiple walls. That tooth may be a much better crown candidate. A photograph of the chewing surface alone rarely tells the whole story.

When Is a Full Crown the Better Option?

A crown may be preferable when there is extensive loss of tooth structure, several compromised cusps, an old restoration with little healthy tooth left, or a fracture pattern that makes partial coverage less predictable.

Sometimes the issue is not just the amount of damage but its location. If a crack, cavity, or previous restoration extends deeply toward the gumline, there may not be enough accessible, healthy structure to support a durable onlay.

Existing crowns also change the equation. Replacing a failing crown with another crown may be more appropriate than trying to redesign a tooth that has already been extensively prepared.

What I do not like is the blanket rule that every large filling automatically needs a crown. We should be able to explain why the selected restoration is necessary for that tooth.

What If the Tooth Is Cracked?

Cracks are one of the reasons this decision becomes complicated. A cracked cusp above the gumline is different from a crack extending down the root. Some cracked teeth can be protected with cuspal coverage; others have a much more guarded prognosis, and a restoration cannot reliably repair every crack.

Symptoms matter. Pain when biting or releasing pressure, temperature sensitivity, swelling, or a history of a sudden fracture can change the evaluation. We examine the tooth, bite, existing restorations, gum findings, and imaging as indicated.

Neither an onlay nor a crown guarantees that a crack will stop progressing. A full crown is not a magic shield, and an onlay is not automatically too weak. The prognosis depends on the actual crack and remaining tooth.

If you have swelling, persistent severe pain, or a broken tooth, schedule a dental examination rather than trying to choose a restoration from an online comparison.

Does a Root Canal Mean You Always Need a Crown?

No—not automatically. But many root-canal-treated back teeth have lost substantial tooth structure from decay, previous fillings, and access preparation. That can make cuspal protection especially important.

The decision depends on the tooth’s position, remaining walls, existing restorations, bite, and how much sound structure is available. A small, conservatively accessed tooth with good remaining support is not the same as a heavily restored molar with two missing cusps.

The goal of root canal treatment is to retain a tooth that can be restored and maintained. The final restoration is part of that success, not an afterthought.

Are Ceramic Onlays as Strong as Crowns?

That question needs context. Modern dental ceramics can perform well in appropriately selected partial- and full-coverage restorations, but material strength alone does not determine clinical success.

Preparation design, remaining enamel and dentin, bonding conditions, restoration thickness, tooth location, chewing forces, grinding habits, and the fit of the restoration all matter.

A ceramic onlay bonded to a well-selected tooth may be an excellent long-term option. A crown on a tooth with inadequate remaining support can still fail. Neither treatment has a guaranteed lifespan, and I would not promise that one always lasts longer than the other.

How Do We Decide at Frangella Dental?

I start with an examination and a discussion about what happened to the tooth. Is an old filling breaking down? Is there a new cavity? Is a cusp cracked? Are we trying to replace a restoration that is failing, or has someone suggested a crown simply because the filling looks large?

Then I evaluate how much tooth is sound, the location of the margins, whether a crack is present, the bite, and whether we can isolate the tooth appropriately for bonding if that is part of the plan.

Digital scans can help us communicate the shape of the tooth and design a restoration. We have discussed how we use iTero digital scanning for crowns and laboratory work. The scanner improves the records we work with; it does not replace the clinical examination.

In some cases, the best answer is still a direct filling. In others, an onlay offers the coverage we need without preparing the entire tooth. And when a crown is indicated, I want to explain what makes it the more predictable choice.

What Does the Procedure Involve?

For an indirect onlay or crown, we generally remove decay or defective restorative material, assess the remaining tooth, prepare the surfaces needed for the chosen design, and capture a scan or impression.

Depending on the treatment and laboratory workflow, a temporary restoration may be needed before the definitive ceramic is placed. At delivery, we evaluate fit, contacts, margins, and bite, then bond or cement the restoration using an appropriate technique.

There may be some short-term sensitivity or tenderness afterward. Persistent pain, a high bite, or symptoms that worsen rather than settle deserve a call to the office.

Is an Onlay Less Expensive Than a Crown in NYC?

Not necessarily. Onlays and crowns are both custom indirect restorations, and their fees depend on the tooth, material, laboratory process, complexity, and whether other treatment is needed.

An onlay should not be chosen because it sounds like a cheaper half-crown, and a crown should not be chosen simply because it is familiar. The most useful comparison is a specific treatment plan with the reason for each option, the expected benefits and limitations, and the actual fee.

Dental insurance coverage also varies. A plan may classify partial-coverage restorations differently from crowns or may have particular documentation requirements. Coverage rules are not a substitute for clinical judgment.

Questions Worth Asking Before You Agree to a Crown

  • What specifically is weakened or damaged about this tooth?
  • Could an onlay or another partial restoration protect it predictably?
  • Is there a crack, and how does that affect the prognosis?
  • How much sound tooth would remain after preparation?
  • Does grinding or my bite affect the restoration choice?
  • What are the tradeoffs, likely maintenance needs, and fees for the reasonable options?

A good treatment recommendation should make sense after the explanation. You should understand what problem we are solving, not just the name of the procedure.

Frequently Asked Questions

Can an onlay fix a broken molar?

Sometimes. If the fracture is limited and there is sufficient healthy structure for a reliable restoration, an onlay may be appropriate. A deeper crack or more extensive damage may require a crown or another treatment.

Is an onlay the same as a three-quarter crown?

They are related partial-coverage concepts, but the terminology and preparation designs are not always identical. Your dentist should explain which surfaces will be covered and why.

Can I replace an old large filling with an onlay?

Possibly. The size of the old filling alone does not decide it. We need to evaluate the remaining cusps, any cracks, recurrent decay, and the bite.

Does a crown prevent a tooth from ever breaking?

No. Crowns can protect compromised tooth structure, but crowned teeth can still develop decay, fractures, gum problems, or other complications. Maintenance and appropriate treatment selection remain important.

The Bottom Line

When a tooth needs more than a filling, the choice is not automatically a full crown. An onlay may provide the necessary protection while preserving more healthy structure in the right case. In another case, a crown may be the safer and more predictable restoration.

My preference is not for one procedure over the other. It is for the most conservative treatment that gives the tooth a reasonable long-term prognosis.

Dr. Andrew Frangella provides restorative, cosmetic, and general dentistry at Frangella Dental in Midtown Manhattan. If you have been told you need a crown and want to understand your options, schedule an examination so we can evaluate the tooth rather than guess from a description.

Smiling woman with bright natural-looking teeth in a bathroom, illustrating cosmetic dentistry and whitening considerations for veneers, crowns, and bonding.

A patient whitens their teeth, loves the result, and then notices something unexpected: one front tooth is still darker. Or the natural teeth have brightened, but the crown beside them looks exactly the same.

That usually is not a failed whitening treatment. It is a materials issue. Peroxide whitening can lighten natural teeth, but it does not predictably lighten the underlying shade of porcelain veneers, ceramic crowns, or composite bonding. That distinction matters before anyone spends money on whitening—or replaces a perfectly serviceable restoration.

Here is how I explain it to patients at Frangella Dental in Manhattan.

Can You Whiten Veneers, Crowns, or Bonding? The Short Answer

Natural teeth: Peroxide-based whitening can often lighten them, although results vary. Porcelain veneers and ceramic crowns: Bleaching does not change their original material shade. Composite bonding and tooth-colored fillings: Their material color does not reliably respond to whitening gel. Implant crowns: They do not bleach either.

Surface staining is a separate issue. Appropriate cleaning or professional polishing can sometimes make a restoration look brighter without changing its underlying color. The American Dental Association’s whitening information explains the distinction between natural teeth and restorations.

Why Natural Teeth Respond to Whitening but Restorations Do Not

Whitening gels commonly use hydrogen peroxide or carbamide peroxide. These ingredients can alter some of the colored compounds responsible for discoloration in natural tooth structure. How much a tooth changes depends on the cause and depth of the discoloration.

Porcelain and composite resin are manufactured restorative materials. Their shades are chosen when the restorations are made. Bleaching cannot simply turn an existing ceramic crown from one shade into another, or remake the color of a bonded composite filling.

There is a nuance worth understanding: the appearance of a restoration can change even when its material shade does not. Plaque, staining at the margins, surface roughness, and sometimes the underlying tooth can influence what you see. That is why I examine a restoration before recommending replacement.

Can a Dental Cleaning Make Veneers Look Whiter?

Sometimes it can make them look cleaner and brighter. That is not the same as bleaching.

Coffee, tea, tobacco, plaque, and other deposits can collect on surfaces or around the edges of dental work. A professional cleaning and polishing approach appropriate to the material may improve the appearance. But polishing cannot turn an originally darker ceramic into a lighter shade.

We also need to be careful with the methods used. An abrasive paste that is appropriate for one surface may not be ideal for another. I would avoid aggressive DIY polishing, acidic whitening tricks, or trying to scrub the color out of a veneer.

What If Your Natural Teeth Are Whiter Than Your Crown?

This is a common situation, especially when the crown is on a front tooth. A crown that blended beautifully when it was placed can stand out after the surrounding teeth are whitened.

First, I want to make sure we are looking at a genuine shade mismatch rather than staining, a dark margin, or a problem with the restoration itself. If the crown is healthy and functional, replacing it solely for color is a cosmetic decision, not an automatic medical necessity.

When the mismatch really is the crown’s shade, whitening strips or stronger gel will not solve it. The choices are generally to accept the difference, adjust the whitening goal for the natural teeth, or discuss replacement if the appearance is important enough to justify the procedure.

Replacement has its own considerations. Removing a crown can involve risks to the underlying tooth, and I would not recommend it casually just because someone wants every tooth to be an extremely bright shade.

Can You Whiten Composite Bonding?

Composite bonding presents a similar problem, but the treatment choices can be different. The composite material itself does not bleach predictably, yet it can develop surface staining over time. Depending on its condition, polishing may help. In selected cases, a small amount of bonding can be repaired or replaced to better match the surrounding teeth.

That does not mean every piece of older bonding needs to come off. I look at the extent of the restoration, the amount of natural enamel, the bite, and whether the color difference is noticeable when you speak and smile.

For patients deciding between restorative options in the first place, our bonding versus veneers guide explains where each treatment makes sense.

Should You Whiten Your Teeth Before Getting Veneers or Crowns?

Often, yes—particularly when the planned restoration will sit next to natural teeth that you would like to brighten.

Porcelain does not change shade after it is bonded. If we match a veneer to your current teeth and you decide to whiten everything six months later, that veneer may suddenly look darker by comparison.

For an elective cosmetic case, I prefer to discuss your desired tooth shade at the beginning. If whitening is appropriate, we can do that first, allow the shade to stabilize, and then choose the restorative color. The interval varies with the whitening method and bonding plan; we should not rush directly from bleaching into adhesive treatment without accounting for that timing.

We also need to look at whether the restoration is actually necessary. If the primary concern is color and the natural teeth are healthy, whitening may be the more conservative starting point. Our article on in-office versus at-home whitening in NYC covers those options.

What About Whitening Strips, Whitening Toothpaste, and At-Home Trays?

Whitening strips and peroxide trays can lighten natural teeth, but they will not recolor a porcelain veneer or crown. If you have several visible restorations, using them without a plan may increase the contrast between your natural teeth and the dental work.

Whitening toothpaste primarily helps remove certain external stains from natural teeth. It does not change the shade selected for porcelain or composite. Abrasivity and the condition of the restorative surface matter, so a product that is marketed as powerful is not automatically the best choice for someone with extensive cosmetic dental work.

Professional whitening allows us to evaluate existing restorations before choosing a method and desired endpoint. It does not make porcelain bleach, but it can help us plan the color of the overall smile intelligently.

One point I emphasize: stronger is not necessarily better. More aggressive whitening can cause sensitivity or soft-tissue irritation without solving a mismatch caused by restorative materials.

When Does a Darker Veneer Actually Need to Be Replaced?

Not every darker-looking veneer needs replacement. I want to know whether the concern is superficial staining, an issue at the margin, a change in the underlying tooth, or a true mismatch with the neighboring teeth.

If a veneer is well bonded, the tooth is healthy, and the only concern is a slight shade difference, leaving it alone may be the most conservative decision. If there is decay, a defective margin, fracture, or a significant esthetic problem, the discussion changes.

Replacement can require additional work on a tooth that has already been prepared. That is one reason I take shade planning seriously before the original veneers are made.

Our recent discussion of veneer costs in NYC also explains why long-term maintenance and possible replacement belong in the treatment decision, not just the initial price.

How to Keep Veneers, Crowns, and Bonding Looking Their Best

The goal is not to bleach the restorations. It is to protect their surfaces and the teeth and gums around them.

  • Brush gently with a suitable fluoride toothpaste and a soft-bristled brush, following your dentist’s specific recommendations.
  • Clean between teeth daily, paying attention to the margins of crowns and veneers.
  • Maintain professional examinations and cleanings so staining and margin problems are identified early.
  • Discuss grinding or clenching; a protective nightguard may be appropriate for some patients.
  • Avoid using teeth to open packaging or bite hard nonfood objects, which can damage restorations.
  • Ask before trying abrasive powders, acidic home remedies, or repeated high-strength whitening treatments.

These habits are not glamorous, but they do more for the long-term appearance of cosmetic dental work than chasing a brighter shade every few months.

Frequently Asked Questions

Will whitening strips damage veneers?

Whitening strips do not bleach the porcelain itself. Whether a particular whitening product is appropriate depends on the condition of the restoration, the exposed tooth surfaces, and your gums. Strips can cause sensitivity or irritation, and existing dental work may create uneven color results. Have the restorations evaluated before using them repeatedly.

Can a dentist whiten an old crown?

A dentist may be able to clean or polish external staining, but cannot bleach the crown’s original ceramic shade to a new one. If the shade truly needs changing, replacement may be an option after examining the tooth and the existing crown.

Can bonding be polished instead of replaced?

Often, if the issue is superficial staining and the bonding is otherwise sound. Deeper discoloration, defective margins, or a significant shade mismatch may require repair or replacement.

Should I whiten before getting a new front crown?

If you want your natural teeth lighter, it is usually worth discussing whitening before the final shade is selected for a new front crown. That helps the crown match the smile you intend to keep.

The Bottom Line

If you have veneers, crowns, or bonding, whitening is not off the table. But we need to know which teeth are natural, which are restored, and what is actually causing the color difference.

Sometimes the right answer is a cleaning. Sometimes it is whitening the natural teeth before we replace an aging restoration. Sometimes it is leaving a healthy veneer or crown alone.

What I would not do is promise that a whitening product can change the color of porcelain or composite. It cannot do that predictably, and patients deserve to know that before treatment begins.

Dr. Andrew Frangella provides cosmetic and general dentistry at Frangella Dental in Midtown Manhattan. If you have questions about whitening around veneers, crowns, or bonding, contact our office for an individualized evaluation.

“How much do veneers cost in NYC?” is usually the first question. It is rarely the most useful one.

Veneers are not a commodity where every case involves the same number of teeth, the same amount of preparation, or the same laboratory work. Two patients can both say they want “veneers” and need completely different treatment.

So before I talk about price, I want to know what we are actually trying to change—and how conservatively we can change it.

What are you paying for when you get porcelain veneers?

A porcelain veneer is a thin ceramic restoration bonded to the front of a tooth. It can change color, shape, proportion, edge position, and—in selected cases—the appearance of mild spacing or alignment problems.

The fee is not just for a piece of porcelain. A well-planned case includes diagnosis, smile design, preparation when needed, provisionalization, laboratory communication, the ceramic work itself, bonding, and adjustment of the final result.

That planning is particularly important in the front of the mouth because a veneer that looks beautiful in isolation can still look wrong if the proportions, gum levels, bite, or neighboring teeth were not considered.

Why veneer prices vary so much

The number of teeth being treated. One discolored or damaged tooth is a different case from redesigning an entire visible smile.

The condition of the teeth underneath. A healthy, intact tooth may allow a very conservative veneer. A tooth with a large old filling, fracture, decay, or existing crown may require a different restoration entirely.

How much the teeth need to change. Small shape corrections are different from trying to mask major crowding, rotation, or bite problems with porcelain.

The laboratory and ceramic work. Front teeth demand careful control of translucency, texture, shade, and symmetry. The technician’s work is a meaningful part of the final result.

Whether other treatment should happen first. Whitening, Invisalign, gum treatment, bonding, or replacement of an old restoration can change the veneer plan—and sometimes reduce the number of veneers needed.

How many veneers do you actually need?

This is one of the biggest reasons online price comparisons can be misleading.

Some patients need one veneer. Some benefit from four, six, eight, or more. And some patients who arrive asking for ten veneers ultimately need far fewer—or none.

I generally look at how many teeth show when you smile naturally, whether the smile is symmetrical, and whether untreated teeth would create an obvious mismatch in color or shape.

I do not like choosing a number because a package says “six veneers” or “ten veneers.” The number should come from the smile, not the sales package.

Do veneers always require shaving down your teeth?

No—but “no-prep” is not automatically better either.

The amount of enamel reduction depends on the starting position, color, shape, and the result we are trying to create. In the right case, preparation can be extremely conservative. In another case, adding porcelain without creating enough room can make teeth look bulky.

What I try to avoid is unnecessarily aggressive preparation of healthy teeth.

That is also why I have been critical of the “Turkey Teeth” trend. Many of the dramatic cases shown online are not conservative veneers at all; they involve substantial tooth reduction for crowns. Once healthy enamel is removed, it does not grow back.

Could bonding be a better—and less expensive—option?

Sometimes, absolutely.

Composite bonding can be an excellent option for a small chip, modest gap, uneven edge, or limited shape correction. It is generally more conservative and can often be completed more quickly than porcelain.

Porcelain becomes more attractive when we need greater control over multiple teeth, larger shape changes, color, surface texture, or long-term stain resistance.

Neither material is “better” in every situation. I recently went deeper into the tradeoffs in our guide to bonding vs. veneers.

What if the real problem is tooth position?

This is where cosmetic treatment planning matters.

If teeth are significantly crowded, rotated, or positioned outside the ideal arch, covering them with porcelain may require more tooth reduction than I am comfortable with. Moving the teeth first with Invisalign can create a much more conservative restorative result.

It may even eliminate the need for veneers on some teeth.

If orthodontic movement is part of the discussion, our guide to how long Invisalign takes explains why treatment time depends on the movements required rather than a fixed number of months.

Should you whiten before choosing a veneer shade?

Often, yes.

Porcelain does not whiten after it is bonded. If the surrounding natural teeth are darker than you want them to be, whitening first lets us establish the color you actually want before matching the ceramic.

This can be especially useful when only a few teeth are being restored.

Our comparison of in-office and at-home whitening explains the options in more detail.

How long do porcelain veneers last?

There is no honest expiration date I can give every patient.

Well-designed porcelain veneers can last many years, but longevity depends on the bite, the amount of remaining enamel, grinding or clenching, oral hygiene, trauma, and how the restorations are maintained.

Veneers are not a lifetime procedure in the sense that you should assume the first set will never need repair or replacement. That future maintenance belongs in the financial decision too.

What should a veneer consultation include?

Before deciding whether veneers make sense, I want to evaluate:

  • the health of the teeth and gums;
  • your bite and any grinding or clenching;
  • the amount and quality of enamel available for bonding;
  • tooth position and whether orthodontics would make treatment more conservative;
  • the number of teeth visible in your smile;
  • existing fillings, crowns, bonding, or discoloration;
  • your expectations for color, shape, and symmetry.

Photos and digital records can help us communicate what you dislike and what you are trying to achieve. The point is not to sell you veneers. It is to determine whether veneers are the right tool.

How should you compare veneer quotes in NYC?

If you are comparing fees, make sure you are comparing the same treatment.

Ask how many teeth are included, whether the restorations are porcelain veneers or crowns, whether provisional restorations are part of the process, what happens if a tooth needs a different treatment once the case begins, and what follow-up is included.

Most importantly, ask why each tooth is being treated.

A lower per-tooth price is not a bargain if you are treating teeth that did not need porcelain in the first place. Conversely, an incomplete plan can become more expensive when additional treatment is added later.

So, what do veneers cost in NYC?

A realistic 2026 NYC range for porcelain veneers is approximately $1,500 to $4,000 per tooth. Some premium Manhattan practices may quote above that range. For perspective, six porcelain veneers at that market range would be roughly $9,000–$24,000, while eight would be roughly $12,000–$32,000 before any separate preparatory treatment.

Those figures are a general New York City market range—not a Frangella Dental fee quote. Your actual cost depends on the number of teeth treated, the complexity of the case, laboratory work, and whether anything should be done before the veneers.

The responsible answer is that the total depends on the case. I do not think publishing one generic number is useful when it can imply that every tooth and every smile requires the same treatment.

After an examination and treatment plan, we can give you a specific fee based on the number of teeth, the restorative design, and any treatment that should happen before the porcelain.

If you are considering veneers, come in with the result you want—not a predetermined number of veneers. Sometimes the best cosmetic plan is porcelain. Sometimes it is bonding, whitening, Invisalign, or a combination that preserves more natural tooth structure.

That distinction matters more than finding the cheapest price per tooth.

Frequently Asked Questions About Veneer Cost in NYC

How much is a full set of veneers in NYC?

There is no standard “full set.” Veneers are usually planned around the teeth that show in your smile rather than automatically treating every tooth. Using a general NYC market range of about $1,500–$4,000 per porcelain veneer, six veneers could roughly total $9,000–$24,000 and eight could roughly total $12,000–$32,000 before any separate preparatory treatment. Those are market examples, not a Frangella Dental fee quote. The right number of veneers should be based on your smile and treatment needs—not a package size.

Does dental insurance cover porcelain veneers?

Usually not when veneers are being done purely for cosmetic reasons. Dental insurance generally does not cover elective cosmetic treatment. There can be situations in which part of a restorative procedure has a dental-health indication, but coverage depends on the specific plan and treatment. We recommend checking the actual benefits rather than assuming veneers are covered.

Are veneers cheaper than dental bonding?

Generally, no. Composite bonding usually costs less initially than porcelain veneers and can be a very conservative choice for small chips, gaps, worn edges, or limited shape changes. Porcelain costs more but may provide advantages when we need greater control over multiple teeth, color, surface texture, or long-term stain resistance. The better comparison is not simply which treatment is cheaper—it is which treatment solves the problem while preserving as much healthy tooth structure as possible. See our bonding vs. veneers guide for a deeper comparison.


Considering porcelain veneers? Dr. Andrew Frangella provides cosmetic and general dentistry at Frangella Dental in Midtown Manhattan. Call (212) 245-2888 to schedule a consultation at 200 W. 57th Street, Suite 1405.

Invisalign

“How long will Invisalign take?” sounds like a simple question. It is also one of the easiest questions to answer badly.

You will see timelines online ranging from a few months to well over a year. All of those can be true. The problem is that Invisalign is not one treatment with one fixed schedule. We are using clear aligners to move teeth through bone, and the amount and type of movement required can be very different from one person to the next.

So when a patient asks me for a timeline, I do not start with an average. I start with what actually has to move.

The short answer: simple cases can be months; comprehensive cases often take longer

A relatively limited case—perhaps a small amount of crowding or spacing—may require only a modest series of aligners. A more involved case that changes the bite, rotates difficult teeth, closes larger spaces, or coordinates both arches can take considerably longer.

For many adult patients, a useful planning range is roughly 6 to 18 months, but that is a planning range, not a promise. Some cases finish sooner. More complex treatment can extend beyond it.

The more important number is the estimate we make after examining you and building the digital treatment plan.

What actually determines how long Invisalign takes?

How far the teeth need to move. Moving one mildly rotated front tooth is different from correcting crowding across an entire arch.

The type of movement. Teeth do not all move equally easily. Certain rotations, root movements, vertical movements, and bite corrections can be less predictable than simply tipping a tooth into a little more space.

Your bite. Sometimes the front teeth are what bothers a patient, but the bite is what determines the treatment. If we straighten the visible teeth without accounting for how the upper and lower teeth fit together, we can create a prettier alignment and a worse functional result.

Whether space needs to be created. Crowded teeth need somewhere to go. Depending on the case, that may involve expansion, carefully planned enamel reduction between selected teeth, moving teeth backward, or occasionally discussing other treatment options.

Your biology. Orthodontic movement is a biological process. Two people with similar-looking teeth do not necessarily move at exactly the same rate.

Wear time matters more than people think

Invisalign only moves teeth while the aligners are being worn.

For most treatment, that means approximately 20 to 22 hours per day, removing the aligners for eating, drinking anything other than water, brushing, and flossing. Your exact instructions may differ depending on the case.

This is where an eight-month treatment plan can quietly become a twelve-month experience. If aligners are consistently left out for long stretches, the teeth may stop tracking with the digital plan. The next tray may not seat properly, and we may need to slow down, repeat a stage, or rescan.

I would rather give someone an honest longer estimate than pretend compliance does not affect the calendar.

How often do you change Invisalign trays?

Many patients change aligners approximately every one to two weeks, but the interval is individualized. Faster tray changes do not automatically mean faster treatment.

The goal is not to get through the plastic as quickly as possible. The goal is for the teeth to complete the planned movement before moving on.

If a tooth is not tracking, simply advancing to the next aligner can compound the problem rather than solve it.

What are Invisalign refinements—and do they mean treatment failed?

No. Refinements are common enough that I discuss them before we start.

The initial series of aligners is based on a highly detailed digital plan, but teeth are living structures, not pieces moving around a computer screen. Near the end of the first series, we evaluate where the teeth actually are versus where we planned for them to be.

If additional movement would improve the result, we take another digital scan and order a refinement series.

That can add weeks or months to the original estimate. It is not necessarily a sign that something went wrong. In many cases, it is how we turn a good result into the result we actually planned.

Can Invisalign be accelerated for a wedding or important event?

Sometimes we can prioritize what matters most visually, but biology does not care about your calendar.

If you have an event coming up, tell us at the beginning. We can discuss what is realistic by that date and whether there are conservative ways to improve the smile along the way. But I would not move teeth faster than I think is appropriate simply to hit an arbitrary deadline.

This is similar to the approach we discussed in our holiday smile timeline: start with the outcome and the available time, then choose treatment—not the other way around.

Why the digital scan helps us estimate the timeline

At Frangella Dental, we use an iTero digital scanner to capture a 3D model of the teeth without conventional impression material.

The scan is part of the Invisalign workup. It lets us evaluate the starting positions, plan movements, and visualize the sequence before treatment begins. That gives us much more useful information than estimating from a quick look at how crowded the front teeth appear.

The simulation is a planning tool, though—not a guarantee that every tooth will follow the animation perfectly or that treatment will finish on the exact predicted day.

What happens after the last Invisalign tray?

Finishing the active aligners is not the end of orthodontic treatment.

Teeth have a tendency to shift after they are moved. Retainers are what protect the result. The type of retainer and wear schedule depend on the case, but long-term retention is part of the plan from the beginning.

This is worth understanding before treatment because “How long does Invisalign take?” really has two answers: there is the active period when we are moving the teeth, and then there is retention to keep them there.

Could bonding or veneers be faster than Invisalign?

Yes—and that does not necessarily make them the better choice.

If the underlying problem is tooth position, Invisalign may let us improve the smile by moving your own teeth rather than adding restorative material. On the other hand, if the teeth are already in good positions and the issue is primarily shape, chips, wear, or color, orthodontics may not be the treatment you need.

We recently compared bonding and porcelain veneers for exactly this reason. Cosmetic dentistry works best when we identify the actual problem instead of forcing every smile into the same solution.

How I give a patient a realistic Invisalign timeline

Before I give you a meaningful estimate, I want to know:

  • What specifically bothers you about your smile?
  • How much crowding or spacing is present?
  • Does the bite need correction?
  • Which tooth movements are likely to be less predictable?
  • Are there existing crowns, implants, missing teeth, or periodontal considerations that affect the plan?
  • Is there an important date we should know about?

Then we can talk about a realistic range, what could extend it, and whether Invisalign is actually the most conservative way to get where you want to go.

The bottom line

If someone tells you exactly how long your Invisalign treatment will take before examining your teeth, they are mostly guessing.

A simple case may be measured in months. A comprehensive case may take a year or longer. Your wear time, the complexity of the movements, how your teeth respond, and whether refinements are needed all influence the finish date.

The goal is not the shortest treatment on paper. It is to move the teeth predictably, finish the bite properly, and end with a result you can maintain.


Considering Invisalign? Dr. Andrew Frangella provides Invisalign and cosmetic dentistry at Frangella Dental in Midtown Manhattan. Call (212) 245-2888 to schedule a consultation at 200 W. 57th Street, Suite 1405.

Close-up natural smile illustrating dental bonding versus porcelain veneers

Patients often come in asking a very direct question: Should I do bonding or veneers?

It sounds like a choice between two cosmetic materials. In reality, it is a choice between two very different ways of treating a tooth.

Composite bonding adds tooth-colored resin directly to the existing tooth. Porcelain veneers use a thin ceramic restoration that is bonded to the front of the tooth after careful planning and, in many cases, some enamel preparation.

Both can look excellent. Both can also be the wrong treatment if they are being used to solve the wrong problem.

Here is how I think through the decision when someone wants to improve chipped, worn, uneven, spaced, or discolored front teeth.

Bonding is usually the more conservative starting point

For a small chip, an uneven edge, a modest gap, or one tooth that is slightly out of proportion, bonding can be a very good treatment.

The biggest advantage is conservation. In many cases we can add material without removing much, if any, healthy enamel. The resin is shaped directly on the tooth, hardened, adjusted to the bite, and polished.

That makes bonding especially useful when the underlying tooth is already healthy and attractive but needs a limited correction.

It is also repairable. If a bonded edge chips years later, we can often repair the affected area rather than replacing an entire restoration.

The tradeoff is that composite resin is not porcelain. Over time it can pick up stain, lose some polish, or chip at thin edges. The more material we add, the more those limitations matter.

Veneers are better when the problem is broader

Veneers become more useful when we are trying to change several things at once: color, shape, proportion, surface texture, spacing, and symmetry across multiple teeth.

Porcelain is more color-stable than composite resin and can hold surface gloss extremely well. It also gives the laboratory and dentist more control when we are redesigning a group of teeth rather than fixing one isolated defect.

But a veneer is not automatically a better version of bonding. It is a more involved restorative treatment, and once healthy tooth structure is removed, that decision is not reversible.

That is why the preparation matters so much. Clinical research has consistently shown that ceramic veneers perform best when they can be bonded primarily to enamel rather than deeply prepared dentin. A recent systematic review found the strongest survival and success outcomes when veneers were bonded to enamel. That is one reason conservative planning is not just cosmetic philosophy; it affects longevity.

A chipped tooth is not the same as a worn-down smile

This distinction gets missed online.

If one front tooth has a small traumatic chip, bonding may be all that is needed.

If several front teeth are shortened because of years of grinding, erosion, or an unstable bite, simply adding composite to the edges without understanding the cause can create repeated fractures.

In those cases, the diagnosis comes first. We need to look at the bite, the pattern of wear, the amount of enamel remaining, the position of the teeth, and whether the back teeth are supporting the bite correctly.

Composite can still be very useful for worn teeth. Recent evidence supports it as a conservative option in appropriate cases, particularly for localized anterior wear, but the long-term result depends heavily on case selection and how the bite is managed.

If the teeth are crooked, neither treatment may be the first move

This is where cosmetic dentistry can become unnecessarily aggressive.

If a tooth is significantly rotated or pushed forward, covering the problem with thick bonding or preparing the tooth heavily for a veneer may create a bulky result or require more enamel removal than we would like.

Sometimes a small amount of orthodontic movement first is the most conservative answer. Moving the tooth into a better position can reduce how much restorative material is needed afterward—or eliminate the need for veneers entirely.

That is also why we use digital scans when planning cosmetic cases. The same iTero technology we use for Invisalign and restorative work helps us evaluate tooth position before deciding how much should be added or removed.

What about staining and tooth color?

If the main concern is color, I usually want to know whether whitening can solve the problem before we start covering teeth.

Whitening changes natural enamel. Bonding and porcelain do not whiten after they are placed.

So if someone is considering bonding or veneers and also wants a brighter shade, the sequence matters. Whitening first may allow us to match the restorative material to the final tooth color instead of doing the restorations first and chasing the shade afterward.

For patients comparing options, our guide to in-office versus at-home whitening explains the differences.

How long do bonding and veneers last?

There is no honest single number because longevity depends on the size of the restoration, the bite, grinding habits, diet, oral hygiene, and how much enamel is available for bonding.

In general, composite bonding should be viewed as maintainable rather than permanent. Small bonded areas may last for many years, but polishing, repair, or replacement is normal over time.

Porcelain veneers can have excellent long-term survival when they are carefully planned, conservatively prepared, and well bonded. Long-term studies of enamel-bonded porcelain veneers have reported high survival over a decade, but that should not be translated into a guarantee for every patient or every tooth.

The useful question is not, “Which one lasts forever?” Neither does.

The better question is, “Which treatment gives this tooth the best balance of appearance, durability, and preservation of healthy structure?”

Bonding is usually better when…

  • The problem is small and localized.
  • You have a minor chip, gap, or uneven edge.
  • The underlying tooth color is acceptable.
  • We can improve the shape without making the tooth bulky.
  • Preserving untouched enamel is the priority.
  • You understand that composite may need periodic polishing or repair.

Veneers are usually better when…

  • Several front teeth need coordinated changes in shape and proportion.
  • Color cannot be predictably corrected with whitening alone.
  • There is enough enamel to plan a conservative preparation.
  • You want a more color-stable and wear-resistant restorative surface.
  • The bite and tooth position make veneers appropriate without aggressive reduction.

And sometimes the right answer is neither

A healthy tooth should not be restored just because we have the ability to restore it.

If whitening solves the problem, whiten. If orthodontics solves the problem, move the tooth. If a tiny chip only needs smoothing, sometimes we simply smooth it.

We recently discussed the opposite end of the spectrum in our article on “Turkey Teeth”, where healthy teeth are sometimes aggressively reduced for full crowns in the name of a fast cosmetic transformation. That is very different from conservative veneer dentistry.

At Frangella Dental, the goal is not to fit every cosmetic concern into the same treatment. It is to use the least invasive option that can predictably accomplish what the patient is asking for.

So: bonding or veneers?

If you have one or two small defects, bonding is often the first option I would want to consider.

If you are changing the color, shape, and proportion of several teeth at the same time, veneers may offer better control and long-term stability.

But the decision should come after we evaluate the teeth—not before. A good cosmetic plan accounts for enamel, bite, tooth position, gum levels, existing restorations, and your expectations before any tooth is altered.

If you want to see the range of problems that can be treated conservatively, our patient gallery includes examples of restorative and cosmetic work completed at Frangella Dental.


Dr. Andrew Frangella provides cosmetic and general dentistry at Frangella Dental in Midtown Manhattan. If you are deciding between bonding, veneers, whitening, or orthodontic treatment, call (212) 245-2888 to schedule a consultation at 200 W. 57th Street, Suite 1405.

Smiling woman with warm holiday lights representing cosmetic dental treatment before the holidays

Every fall, we start getting some version of the same question: Is there still enough time to fix my smile before the holidays?

Usually, yes — but the answer depends entirely on what you want to change.

Some improvements can happen in a single visit. Others need a few weeks. And some treatments simply should not be rushed because there is a holiday party on the calendar.

Here’s how I think about the timeline when a patient sits down and tells me, “I want my smile to look better by Thanksgiving, Christmas, or New Year’s.”

First: what actually bothers you?

“I don’t like my smile” can mean ten different things.

For one person, the teeth are healthy and straight but darker than they used to be. Another has one chipped front tooth that catches their eye in every photograph. Someone else may have crowding, worn edges, old bonding, uneven gum levels, or several things happening at once.

That distinction matters because the fastest treatment is not automatically the right treatment.

Before doing cosmetic dentistry, we first make sure the teeth and gums are healthy and figure out exactly what is creating the appearance you want to change. Sometimes the answer is much simpler than the patient expected.

If your teeth just need to look cleaner and brighter

Timeline: days to a few weeks.

If it has been a while since your cleaning, start there. Stain and buildup can change the appearance of teeth more than people realize, particularly around the gumline and between teeth.

If the teeth are healthy and the issue is color, whitening is one of the quickest ways to make a noticeable change without altering the tooth structure.

The important part is setting expectations. Whitening changes the color of natural enamel. It does not change the color of crowns, veneers, or existing tooth-colored fillings. If you have restorations on your front teeth, we need to account for that before whitening so you don’t end up with mismatched shades.

If you have a chip, uneven edge, or small gap

Timeline: often one or two visits.

Composite bonding can be extremely useful for small, specific problems. Tooth-colored resin is shaped directly on the tooth to repair a chip, close a modest space, or improve an uneven edge.

It is conservative because, depending on the situation, little or no healthy enamel needs to be removed.

But bonding has limits. Trying to solve a large alignment, bite, or color problem with excessive composite can create bulky teeth and a result that is harder to maintain. I would rather tell someone that bonding is not the right tool than make every cosmetic problem fit the fastest treatment.

If you are considering veneers

Timeline: generally several weeks, after proper planning.

Veneers can change color, shape, proportion, spacing, and symmetry at the same time, which is why they can create a dramatic result relatively quickly.

That does not mean they should be treated as an emergency makeover.

The planning matters. We need to evaluate your bite, the amount and position of enamel, your gum levels, the shape you are trying to achieve, and whether veneers are even necessary on every tooth you are considering.

There is also an important difference between conservative porcelain veneers and aggressively preparing healthy teeth for full crowns. We recently wrote about that distinction in our discussion of “Turkey Teeth”. Once healthy tooth structure is removed, it does not grow back.

If veneers are appropriate, I want enough time to plan them properly rather than designing treatment backward from a party date.

If the real problem is tooth position

Timeline: months, not weeks.

This is where holiday deadlines can push people toward the wrong decision.

If teeth are crowded, rotated, or positioned in a way that is driving the cosmetic problem, orthodontic treatment such as Invisalign may be the most conservative solution because we are moving your own teeth rather than covering the problem with restorative material.

Some patients notice improvement fairly early, but meaningful orthodontic movement takes time. Starting Invisalign now may absolutely improve your smile over the coming months, but I would not promise a finished orthodontic result by a nearby holiday simply because that is the date we would like.

We use our iTero digital scanner to evaluate tooth position and plan Invisalign without conventional impressions.

Sometimes the best plan uses more than one treatment

Cosmetic dentistry is often better when we do less of each thing.

A little orthodontic movement can put a tooth in a position that requires less bonding or less porcelain. Whitening first can mean fewer restorations need to be replaced for color. Correcting inflamed gums before cosmetic work can completely change where the final tooth should end.

That is why I am cautious when someone arrives with a treatment already selected from Instagram or TikTok. Start with the outcome you want, not the procedure you think you need.

So what can realistically be done before the holidays?

If you came in this fall, this is the rough way I would think about it:

  • Cleaning and stain removal: very realistic.
  • Professional whitening: usually realistic.
  • Small chips, gaps, or edge corrections with bonding: often realistic.
  • Replacing a limited number of unattractive old restorations: often realistic, depending on the case.
  • Porcelain veneers: potentially realistic, but only if there is adequate time for diagnosis, planning, preparation, and laboratory work.
  • Invisalign: realistic to start; whether it can be completed depends on how much movement is required.

And occasionally the right answer is: don’t do anything yet.

If I think rushing treatment compromises the result or removes healthy tooth structure unnecessarily, I would rather have you look the same in this year’s holiday photos and have the right smile next year.

The earlier we look, the more options you have

You do not need to walk into a cosmetic consultation knowing whether you need whitening, bonding, veneers, or Invisalign. That is our job to help you figure out.

Bring in what bothers you. We can look at your teeth, your bite, your existing dental work, and your timeline, then tell you what is realistic — including when the simplest option is the best one.


Thinking about improving your smile before the holidays? Dr. Andrew Frangella provides cosmetic and general dentistry at Frangella Dental in Midtown Manhattan. Call (212) 245-2888 to schedule a consultation at 200 W. 57th Street, Suite 1405.

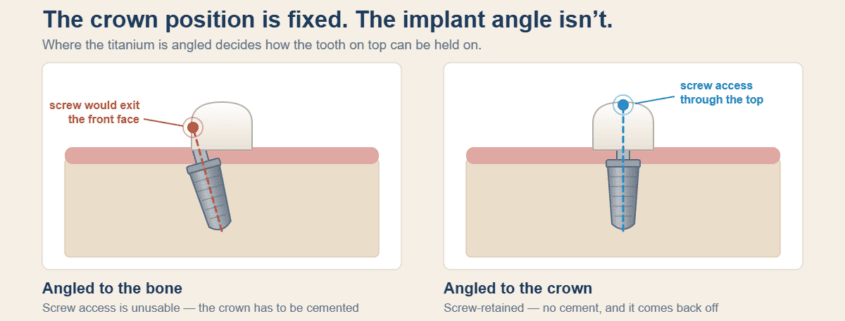
Diagram comparing two implants under identical crowns: one angled to the bone, whose screw channel exits the front face of the crown, and one angled to the crown, whose screw access exits through the biting surface.

Two implants can both be textbook successes by the usual definition — fused to the bone, no pain, no infection, stable for years — and only one of them can be restored well.

That gap is the part of implant dentistry patients almost never hear about, because the number everyone quotes is the survival rate. Implant survival is genuinely high. But survival only measures whether the titanium stayed put. It says nothing about whether the tooth on top of it looks right, cleans easily, or can be repaired in fifteen years without cutting it off.

Position is what decides that. And position has to be planned backward from the crown.

What “successful” usually means

When an implant is placed, the biological goal is osseointegration — bone growing into direct contact with the titanium surface. That process takes roughly three to six months, and when it works, the implant is locked in.

Osseointegration is a low bar for a restoration, though. An implant placed two millimeters too far toward the cheek will integrate beautifully. An implant tipped at the wrong angle will integrate beautifully. Bone doesn’t know or care where the crown was supposed to go.

So an implant can be a surgical success and a restorative headache at the same time. That’s not a rare edge case — it’s the most common way implant treatment quietly underperforms.

Three dimensions, all decided at surgery

Once the implant is in the bone, its position is essentially permanent. Everything the final crown can and can’t be was determined in that appointment.

Side to side. An implant needs roughly 1.5 mm of space between it and a neighboring natural tooth, and about 3 mm between two adjacent implants. Crowd that space and the bone between them resorbs — and the bone is what holds up the gum triangle between your teeth. Lose the bone, lose the papilla, and you get a dark triangle that no amount of ceramic work will fill. This is a bone-height problem masquerading as a cosmetic one.

Depth. The implant sits below the gumline, and how far below shapes the emergence profile — the way the crown widens out of the tissue the way a real tooth does. Too shallow and you see metal or get an abrupt, flat-looking crown. Too deep and the crown margin ends up somewhere no one can clean or access.

Angle. This one has the largest downstream consequence, and it’s the least intuitive. A crown can be held on in one of two ways: a screw through the biting surface, or cement. If the implant is angled so that the screw channel would exit through the front of the tooth, a screw-retained crown is off the table, and the restoration gets cemented instead.

Why the angle matters more than it sounds

Cement is the problem. When a crown is cemented onto an implant below the gumline, excess cement can get pushed into the tissue where it can’t be seen and doesn’t come out on its own.

In a 2009 endoscopic study, excess cement was found in association with signs of peri-implant disease in about 81% of the cases examined — and once the cement was removed, the signs of disease resolved in roughly 74% of those implants. A cross-sectional study published in 2025 found the same relationship. Cement left behind under the gum is one of the more preventable causes of implant inflammation and bone loss.

A screw-retained crown avoids this entirely. It also comes off. If the porcelain chips in year twelve, a screw-retained crown is unthreaded, repaired, and put back. A cemented one usually has to be destroyed to be removed.

None of that is a choice made at the crown appointment. It’s a choice made by where the implant was angled months earlier.

The path of least resistance points the wrong way

Here’s the tension: the position that’s best for the crown is often not the position that’s easiest for the surgery.

Bone isn’t evenly distributed. After a tooth is lost, the ridge tends to resorb from the outside in, so the widest, safest bone frequently sits toward the tongue or palate — or the ideal restorative angle would run the implant right through the thin outer plate of bone. Planning from the crown backward means you sometimes have to graft, use a narrower implant, or accept a more technically demanding placement in order to end up where the tooth needs to be.

Planning from the bone forward is faster and has fewer surgical complications. It also produces implants that are harder to restore.

Neither approach is dishonest. They’re just optimizing for different endpoints — and which endpoint gets optimized depends a lot on who is holding the handpiece and whether that person is the one who has to deliver the crown.

Where doing both phases actually changes something

I place and restore implants in this office, which means I’m the one who has to live with my own surgical decisions six months later.

I want to be careful about what I’m claiming here. I’m not aware of good head-to-head evidence that one-clinician implant care produces better long-term outcomes than a well-coordinated surgeon-and-restorative-dentist team. Plenty of two-office teams do excellent work, and a specialist surgeon doing high volume brings real advantages. So this isn’t a claim about outcome data — it’s a claim about incentives and information.

What changes is that there’s no handoff. I’ve already planned the crown before I plan the surgery — the 3D scan and the digital impression get merged, and the implant position is designed from the finished tooth backward, not the other way around. If that requires grafting, I know that in advance because I’m the one who’s going to be stuck without it. And if something about the position ends up compromising the restoration, there’s no ambiguity about whose problem it is.

Consolidation isn’t automatically better. But it does remove the seam where restorative information tends to get lost.

What to ask, wherever you have it done

If you’re considering an implant — here or anywhere — these are fair questions:

  • Will the position be planned from a 3D scan and a digital impression of the final tooth, or from the bone alone?
  • Will the crown be screw-retained or cemented? If cemented, why?
  • Do I need grafting to put the implant where the crown should go?
  • Who restores it, and how do the two of you communicate about position?

A good answer to these is a better predictor of how the implant will look and last than any survival statistic.


Have questions about implants? Dr. Andrew Frangella places and restores dental implants at Frangella Dental in Midtown Manhattan. Call (212) 245-2888 or schedule a consultation at 200 W. 57th Street, Suite 1405 — steps from Columbus Circle.

References

  • Wilson TG Jr. “The positive relationship between excess cement and peri-implant disease: a prospective clinical endoscopic study.” Journal of Periodontology, 2009. PubMed
  • Montevecchi M, et al. “Excess cement and peri-implant disease: a cross-sectional clinical endoscopic study.” Journal of Periodontology, 2025. PubMed
Turkey teeth explained: they're not veneers, they're crowns — and that changes everything. Frangella Dental, New York City cosmetic dentistry.

You’ve seen the before-and-afters. Someone flies to Istanbul, spends a few thousand dollars, and comes back a week later with a full set of bright white teeth for a fraction of what it would cost here. The results look good in the video.

The problem isn’t that the work happens abroad. There are excellent clinicians in Turkey, and plenty of mediocre ones in New York. The problem is what’s being done to the teeth, and the fact that most patients don’t understand it until years later.

They’re usually not veneers

This is the part that gets lost. “Turkey teeth” are almost always marketed as veneers. In most cases they are crowns.

The difference matters enormously. A veneer is a thin ceramic shell bonded to the front of a tooth. A crown covers the entire tooth on all sides, which means the tooth underneath has to be reduced to a peg first.

The numbers are stark. A 2002 study in the Journal of Prosthetic Dentistry measured exactly how much tooth structure different preparations remove. Veneers took away roughly 3% to 30% of the crown of the tooth. Full-coverage crowns took 63% to 72%. Preparing a tooth for a metal-ceramic crown removed about 4.3 times more tooth structure than preparing it for a facial veneer.

So when someone says “I got veneers” and their teeth were filed to points beforehand, they didn’t get veneers. They had roughly two-thirds of each tooth removed and replaced with ceramic.

Enamel does not grow back

This is the whole issue in one sentence. Bone heals. Gums heal. Enamel is not living tissue — once it’s gone, it is gone permanently.

That means the decision is irreversible in a way most cosmetic procedures aren’t. A patient who has twenty healthy front and side teeth crowned has committed to having crowns on those teeth for the rest of their life. Not because the first set failed, but because there is no longer enough tooth left to do anything else. Every future problem gets solved with another crown, a root canal, or an extraction.

Someone who has this done at 25 will likely be redoing that work three or four times before they’re 70. Crowns don’t last forever.

What happens to the nerve

Cutting a tooth down generates heat and removes the insulating layer that protects the pulp. Sometimes the nerve doesn’t survive it.

A prospective study in the International Endodontic Journal tracked teeth after crown preparation and found pulp necrosis in about 9% overall — 5% in teeth that were structurally intact beforehand, 13% in teeth that already had decay or fillings. Older literature puts the range anywhere from 3% to 25%. Longer term, studies of metal-ceramic crowns found pulp vitality survival of roughly 84% at ten years and 81% at fifteen.

Read those percentages against a full-mouth case. If someone has twenty teeth prepared, a 9% necrosis rate means you’d expect one or two of them to need root canal treatment — and that’s assuming careful technique and healthy teeth going in. Aggressive preparation on twenty perfectly healthy teeth stacks the odds badly.

The failures also tend to be silent. A tooth under a crown can die without hurting. Patients often find out months or years later, when it abscesses.

The follow-up problem

Even good work needs adjustment, monitoring and repair. A crown seated slightly high, a margin that irritates the gum, a bite that needs refining — these are normal and fixable, but they need a dentist who can see you.

If your dentist is 5,000 miles away, that doesn’t happen. Reported cases in the UK include patients returning within months with bleeding gums, infection and active pus around teeth that were healthy before they left. At that point the original clinic is unreachable and unaccountable, and the local dentist inherits a problem they didn’t create.

What it costs to undo

There’s often no undoing it. There’s only managing it.

If a crowned tooth’s nerve dies, that’s root canal treatment plus a post and core plus a new crown — for one tooth. If the tooth has been reduced too far to hold a crown, it comes out, and replacing it means an implant, which involves surgery, healing time and a new restoration.

Multiply by however many teeth are failing at once. It is entirely possible to spend several times the original “savings” on repair, and end up with fewer natural teeth than you started with.

What conservative cosmetic work actually looks like

Real veneers are thin. Minimal-prep designs run about 0.2 to 0.5 mm; conventional veneers about 0.3 to 1.0 mm. In many cases little or no enamel comes off at all, and where it does, the tooth stays structurally intact underneath.

Not everyone is a candidate. Heavily filled teeth, significant crowding or a badly worn bite may genuinely call for crowns, and sometimes orthodontics or whitening gets you most of the way there without any restorative work at all. But the honest sequence is: fix what’s actually wrong first, then use the least invasive option that gets the result.

If a treatment plan involves crowning healthy teeth for appearance alone, that deserves a second opinion — here or anywhere.

If you’ve already had it done

Don’t panic, and don’t ignore it. Get a full exam with X-rays so someone can check the margins, the gum health, and whether any of the nerves have died quietly. Problems caught early are far cheaper and far less destructive than problems found when a tooth abscesses.

If you’re considering going, get a consultation here first — not to talk you out of it, but so you know what’s actually being proposed and can ask the right questions before anyone picks up a handpiece.


This post is general educational information, not medical or dental advice, and doesn’t replace an exam. If you have concerns about existing crowns or veneers, give us a call and we’ll take a look.